
Updated October, 2026 by Dr. Dawson
You buy wider shoes. You loosen the laces. You start choosing restaurants based on how far you have to walk from the parking lot.
At some point, that bump beside your big toe starts making more decisions than it should.
The good news is that having a bunion does not automatically mean you need surgery. There are practical ways to make your foot more comfortable, and several effective surgical options when those changes are no longer enough.¹
TLDR
A bunion is a change in bone alignment, not simply an extra lump of bone.¹
Shoes, padding, and sometimes inserts or spacers can help with discomfort. They do not reliably straighten an established bunion.¹ ²
Surgery is worth discussing when pain keeps interfering with life despite reasonable nonsurgical treatment.¹
Modern surgery includes both minimally invasive and open techniques. The best choice depends on your foot and the problem being corrected.³ ⁴
Walking after surgery and being fully recovered are different milestones. Some patients can walk in protective footwear right away, but healing still takes time.⁵
What exactly is a bunion?
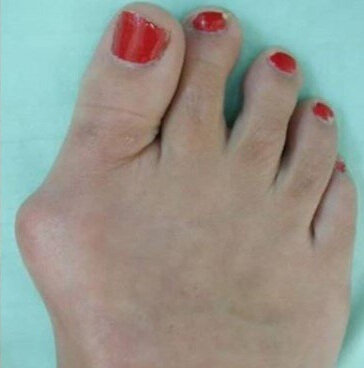
A bunion forms when the big toe leans toward the second toe and the long bone behind it shifts out of alignment. The joint then sticks out along the inside of the foot. The medical name is hallux valgus.¹
Think of a cabinet door hanging crooked. The corner sticking out is what you notice, but sanding that corner down does not fix the way the door hangs.
That is why correcting a bunion usually involves more than shaving off the bump.
Why did I get one?
Usually, several factors are involved. The foot structure you inherited, how your joints move, and the shoes you wear can all play a part.⁶
Tight shoes can squeeze the area and make symptoms worse. But plenty of people with bunions have never spent a day in high heels.
So, no, this is not necessarily punishment for your footwear choices in your 20s.
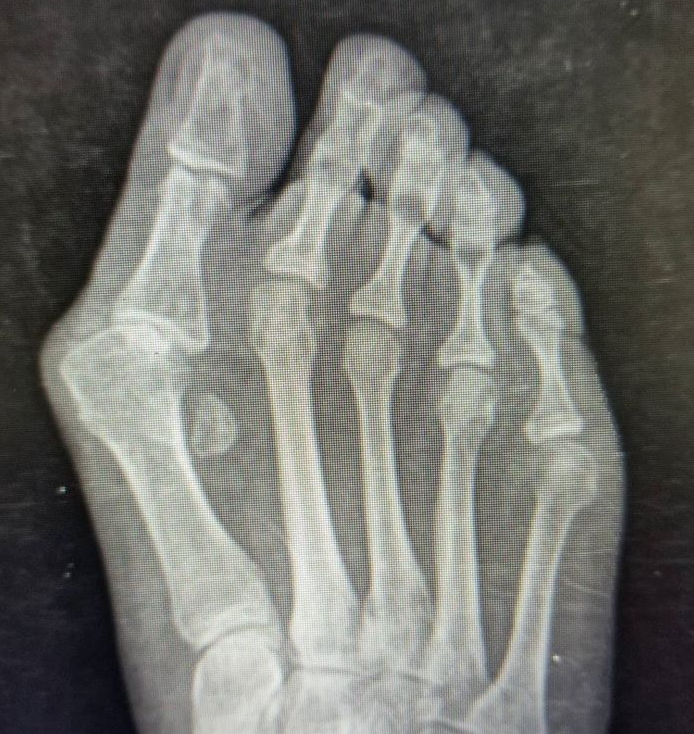
This condition is not just cosmetic. It is associated with pain, decreased walking efficiency, increased fall risk in elderly patients, and reduced quality of life.³
Common companions: Pain under the big toe joint is often sesamoiditis. Numbness between the lesser toes can be Morton’s neuroma.
Pediatric Bunions: A Different Consideration
Juvenile or adolescent hallux valgus behaves differently from adult bunions. The deformity is often more flexible but progresses with growth, especially if there is ligamentous laxity or flatfoot.
Signs parents may notice include:
Shoe fit problems
Overlapping toes
Visible deviation of the big toe, even without pain
Pain is not always the first symptom in children, which is why careful monitoring is important.
Management tips for pediatric bunions:
Conservative care first: Shoes with wide toe boxes (Topo works well here too), orthotics for underlying flatfoot, and activity modification.
Avoid splints for “correction”: No evidence for durable benefit, and they may cause compliance issues.
Delay surgery until skeletal maturity unless symptoms and deformity are severe. Early surgery carries a higher recurrence risk.²⁰
Education is key: Families should understand progression and realistic expectations for long-term management.
Conservative Care: Relief, Not Cure
Nonoperative care aims for symptom relief, better shoe fit, and slower progression — not reversal of deformity in adults.⁶ ⁷
What I recommend
Shoes: Topo is my first choice due to its combination of a wide toe box, secure midfoot, and mild rocker sole. Altra is an excellent alternative with zero-drop and a foot-shaped toe box, especially for casual wear. HOKA Bondi and Skyline provide rocker-sole forefoot offloading for active patients. Brooks Ghost Max 3 and New Balance Fresh Foam More are strong cushioned trainers with roomy toe boxes that have tested well in bunion comfort reviews.⁶ ²² Several studies have shown that footwear with adequate toe box width and cushioning can significantly reduce bunion-related pain and improve gait efficiency.²²
Orthoses: Custom or prefabricated OTC like Powersteps with a Morton’s extension to protect the joint, improve comfort, redistribute plantar pressures, and address coexisting flatfoot or metatarsalgia.
Activity modification: Reducing activities that exacerbate forefoot loading.
NSAIDs and icing as needed for inflammation control.
What I don’t recommend
Bunion splints: While they may temporarily reduce pain or toe overlap in a shoe, they do not change bone position long-term. Evidence shows no lasting structural benefit in adults.⁶ ⁷
What helps, and what it can actually do
Roomier shoes + thin padding
Less squeezing and rubbing. The bunion itself remains.¹
Inserts
May improve comfort and pressure distribution. They do not permanently straighten the bones.²
Spacers + splints
May help symptoms. Lasting correction is not reliably established.²
Surgery
Can correct alignment when symptoms justify it. Requires healing time and carries risks.¹
Shoe comfort and mechanics: If arch or heel pain limits your walks, compare with plantar fasciitis. Nail edge tenderness from crowding fits the pattern in ingrown toenails.
When is it time to get your bunion checked?
Make an appointment if pain keeps returning, reasonable shoes still hurt, or you are changing your activities because of your foot.¹
An evaluation should include a conversation about where it hurts and what you want to get back to. An examination and standing X-rays help show the alignment and whether the joint itself has other problems.³ ⁵
A photo shows the bump. It does not tell the whole story.
How do you know when surgery is worth it?
A useful question is: “Am I managing this comfortably, or am I organizing my life around it?”
Surgery becomes worth discussing when appropriate nonsurgical treatment has not provided enough relief. Difficulty walking, exercising, working, or finding comfortable shoes can all be part of that conversation.¹
You do not have to wait until the toe is dramatically crooked. You also do not need surgery simply because the bump is visible.
The purpose is to improve comfort and function. Operating only to change how a foot looks exposes you to risks without the same functional reason for treatment.⁷
What does bunion surgery actually do?
Most operations work by changing the position of the bones and balancing the tissues around the joint. The correction is often held with screws, a plate, or another implant while it heals.⁵ ⁸
There are several ways to do that. The names can sound like a menu written in another language, but the basic choices are easier to understand.
Bone realignment: moving the pieces into a better position
An osteotomy is a controlled cut in a bone. The surgeon repositions it and secures it while it heals.
Depending on the correction needed, the cut may be near the end of the metatarsal, farther along the bone, or combined with a small correction in the big toe itself. You may hear names such as chevron, scarf, transverse osteotomy, or Akin.⁹
The important question is what the procedure will accomplish for your foot.
Lapidus: correcting through a joint farther back
A Lapidus procedure realigns and fuses the joint at the base of the first metatarsal, farther back than the visible bunion. It can be useful when that joint and the surrounding alignment need to be addressed.⁸
It does not fuse the big toe joint. Those are different joints in different places.
True minimally invasive construct allowing triplanar correction through a few small 1-2 stitch incisions.¹⁶
Early results indicate it works well with my early boot protocol, as with most minimally invasive techniques the literature is fairly new and emerging. However, anecdotally my fusion and success rates are equally as high as my open techniques.
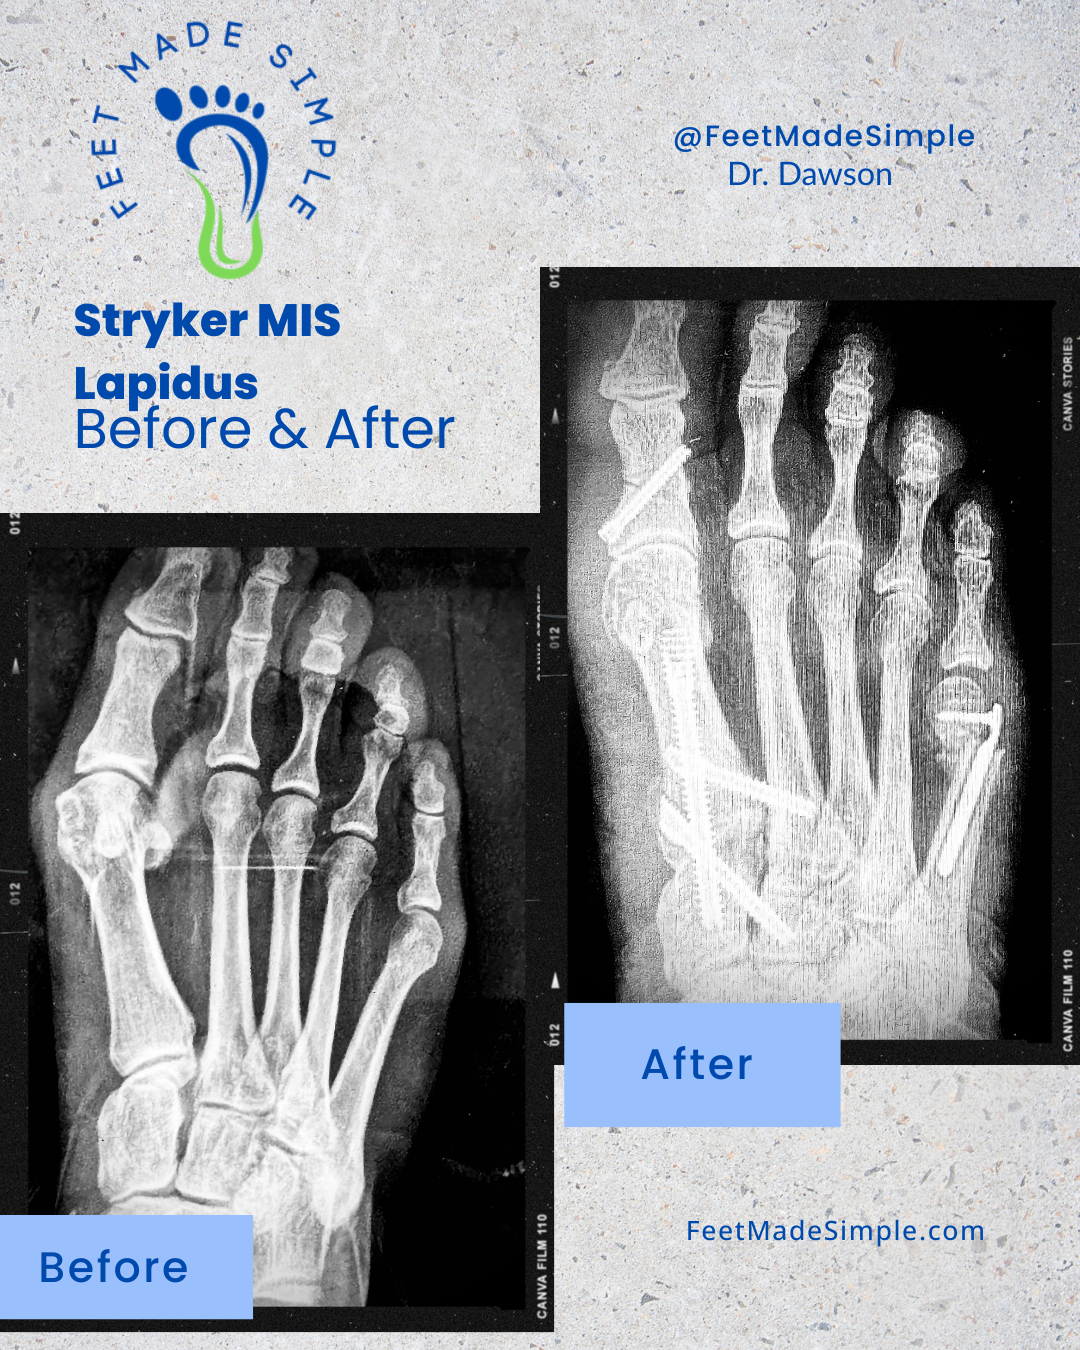
Stryker ProStep MIS hardware, also pictured is the Stryker MIS tailors bunion nail
This patient was allowed to bear weight on the foot the day of surgery in a walking boot
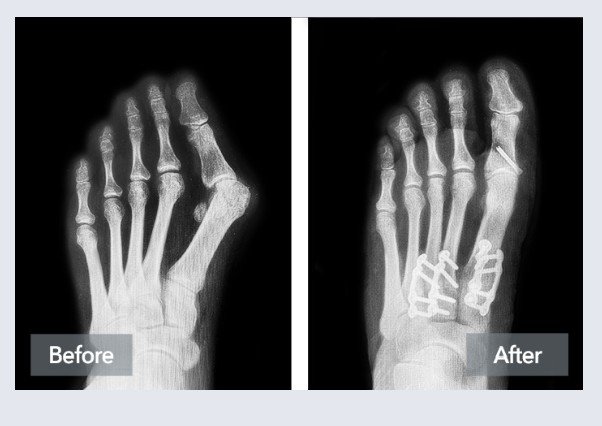
A version of the Lapiplasty called the Adductoplasty
While this specific technique is for SEVERE bunions, it shows the power of the lapidus technique using the Lapiplasty hardware
Big toe joint fusion: an option for a damaged joint
If the big toe joint has substantial arthritis or certain other problems, straightening the bones alone may not address the pain. A fusion can be an appropriate option in selected cases.³ ⁹
That does mean giving up movement at that joint. The tradeoff is treating a joint that has become painful or unreliable.
Bunion operations in plain English
Osteotomy: move the bone
A controlled cut allows the surgeon to reposition the bone. Can be performed through an open or minimally invasive approach.⁴ ⁹
Lapidus: realign and fuse farther back
Addresses the joint at the base of the first metatarsal. The big toe joint remains separate.⁸
Big toe joint fusion: treat a damaged joint
Can be appropriate for significant arthritis or certain complex problems. The fused joint no longer bends.³ ⁹
Small incision or larger incision?
That describes how the surgeon reaches the bones. It is a separate question from what correction your foot needs.
What about minimally invasive bunion surgery?
Minimally invasive surgery, or MIS, allows the surgeon to correct the bones through smaller incisions using specialized instruments. It is still bone surgery, even if the openings in the skin are small.⁵
Think of renovating a room through a smaller doorway. The doorway changes how you get the work done. The work inside still needs to be done properly.
Some minimally invasive operations use a chevron shaped cut. Others use a transverse cut across the bone. Fixation also varies. “MIS” describes a group of techniques rather than 1 identical operation.⁴ ¹⁰
Does it work as well as traditional surgery?
Modern MIS techniques have encouraging evidence behind them.
A randomized study found comparable results between minimally invasive and open chevron surgery at 5 years.⁴
A larger study of 729 feet treated with a minimally invasive transverse osteotomy found improvements in pain, walking, and alignment at an average follow-up of 2.6 years. The reported X-ray recurrence rate was 4.5%, and the complication rate was 6.1%. Those results describe that particular study, not a guarantee for every operation.¹⁰
That makes MIS a legitimate option. It does not mean every bunion should be treated through the smallest possible incision.
A 2026 study of severe bunions also highlighted the importance of how flexible the deformity was before surgery. Both techniques studied improved alignment, but recurrence was higher in the transverse group, which contained more stiff deformities.¹¹
My perspective
I now favor minimally invasive correction for many suitable patients, often using a transverse bone cut and an implant inside the bone to hold the correction.
But the bigger conversation is about finding the operation that fits your foot. An experienced surgeon should be able to explain why they recommend a particular approach and what alternatives make sense.
Can you walk after bunion surgery?
Sometimes, yes. Some modern procedures allow protected walking in a surgical shoe or boot immediately after surgery. Others require a period of keeping weight off the foot.⁵ ⁸
In my practice, I commonly allow protected walking from day 1 after my usual MIS correction when the patient’s health and the repair support it.
That is permission to get around safely while healing. It is not a prescription for 10,000 steps.
The implant holds the correction while the bone heals. It does not make the bone instantly healed.
“I can walk” is not the same as “I'm healed”
Early protected walking
Getting around in the prescribed shoe or boot, within your surgeon's limits.
Returning to regular shoes
A separate milestone based on healing, swelling, and the operation performed.
Long walks, full work shifts, and exercise
More demanding goals that need their own recovery plan.
Ask for a plan that matches your life, not just a date when you can “walk again.”
The below are other bunion corrections you may have heard about in your research.
| Procedure | Best For | Key Points | Drawbacks |
|---|---|---|---|
| Distal Chevron Osteotomy | Mild deformity, younger patients | Quick recovery, good pain relief | Limited correction power, not for severe deformities |
| Scarf Osteotomy | Mild-to-moderate | Allows more correction than chevron, stable fixation | Larger incision, less triplanar correction |
| Akin Osteotomy | Often adjunctive | Corrects hallux valgus interphalangeus | Rarely standalone |
| Proximal Metatarsal Osteotomies | Moderate-to-severe without hypermobility | Greater correction than distal | Longer recovery, higher recurrence if instability unaddressed |
| MTP Joint Arthrodesis | Arthritic, salvage cases | Eliminates pain in end-stage arthritis | Loss of joint motion |
How long does recovery take?
Recovery is a series of milestones.
Getting to the bathroom, wearing a regular shoe, standing through a workday, and going for a run all ask different things of your foot.
Early recovery: protect the repair
Plan on protective footwear, dressing care, follow-up appointments, and time to rest.
Arrange help with the jobs that keep you standing. Grocery shopping, laundry, childcare, and an enthusiastic dog do not pause just because you have had surgery.
Returning to shoes: let healing lead
Many MIS protocols use a protective shoe for approximately 6 weeks, but the timing varies. Your examination, X-rays, swelling, and any additional procedures help determine when it is appropriate to change footwear.⁵
Even once you are cleared for regular shoes, a roomy sneaker may feel good before a dress shoe does.
Returning to normal life: expect gradual progress
Swelling can continue for months. Full recovery may take 6 to 12 months, even though you can often resume useful activities much sooner.⁵
Ask about your actual routine. “When can I work?” means something different for someone at a desk than for someone standing through a 12-hour shift.
Driving also needs its own discussion, particularly after right foot surgery or while taking sedating pain medication.
What can go wrong?
Possible complications include infection, nerve irritation, stiffness, persistent pain, problems with bone healing, uncomfortable hardware, and the bunion returning. Occasionally, another procedure is needed.⁵
Smaller incisions do not make those risks disappear.
Before deciding, ask what your surgeon sees as the biggest risks for your foot, how likely they are, and how they would be managed.
A few common questions
Can you just shave the bump off?
Usually, shaving alone would leave the underlying alignment problem in place. It may be part of an operation, but the correction often requires repositioning bone as well.¹ ⁵
Will I need the screws taken out?
Usually, implants can stay in place. Removal may be considered if they become painful or cause another problem. It is not an automatic second stage of recovery.⁵
Can a bunion come back?
Yes. Recurrence can happen after different types of surgery. A change on an X-ray does not always mean the pain has returned or that another operation is needed.⁵
Should I have surgery before it starts hurting?
A painless bunion is not automatically a reason to operate. Symptoms, function, and individual circumstances should guide the discussion.⁷
What if my child has a bunion?
Growing feet need their own assessment. Remaining growth, symptoms, and the risk of recurrence affect treatment decisions. Adult surgical advice should not simply be applied to a child.³
What I want you to take away
You do not need to become an expert in bunion surgery to make a good decision.
Start with comfortable shoes and practical ways to reduce irritation. If your foot still limits your life, get it assessed and ask someone to explain the options in plain English.
The goal is a comfortable, useful foot that lets you get back to the things you enjoy
Bottom Line for Pediatrics
Focus on comfort and shoe fit.
Monitor for progression, especially during growth spurts.
Delay surgery until skeletal maturity unless symptoms are severe.
Use orthotics if flatfoot is present.
Avoid splints — no lasting benefit and potential compliance issues.
Bunion FAQ
Do bunion splints fix the bone?
No. They may offer comfort but do not realign the first metatarsal. Alignment changes require surgery when symptoms and function demand it.¹
When is surgery reasonable?
When pain or shoe conflict limits life despite shoe changes, orthoses, and activity adjustments. Imaging and exam guide the procedure choice.¹
Will shoes alone stop progression?
Shoes can improve comfort and reduce symptoms. Progression depends on anatomy, ligament laxity, and load.¹
¹ References align with the main article’s citations from peer‑reviewed sources including JFAS, APMA, and AOFAS.
🦶 Recommended Products for Bunions
These items are listed for education and reference only. They are not a substitute for medical advice. Please see your podiatrist for specific recommendations. I may receive a commission if you purchase through these links, at no additional cost to you.
👟 Shoes
- Topo Ultraventure 4 – Trail shoe with wide toe box to reduce bunion irritation
- Topo Atmos – Maximalist shoe with roomy forefoot
- Altra Torin 8 – Zero-drop shoe with naturally wide forefoot fit
🦾 Orthotics
- Powerstep Pinnacle Maxx – Helps control pronation contributing to bunion pressure
Research & References
Good foot care advice should have more behind it than a convincing sales pitch. These studies, clinical reviews, and professional resources informed this guide. References reviewed in October 2026.
Professional Patient Guidance
Bunions
American College of Foot and Ankle Surgeons. Foot Health Facts.
Explains bunion symptoms, practical nonsurgical care, and when surgery may be worth considering.
Read Patient Guidance ↗Systematic Review & Meta-analysis | 2022
Effectiveness of Nonsurgical Interventions for Hallux Valgus
Hurn SE, Matthews BG, Munteanu SE, Menz HB. Arthritis Care & Research. 2022;74(10):1676–1688. doi:10.1002/acr.24603.
Reviews nonsurgical treatments, including their potential for symptom relief and the limitations of the available evidence.
View Systematic Review ↗Clinical Consensus Statement | 2022
The American College of Foot and Ankle Surgeons Clinical Consensus Statement: Hallux Valgus
Meyr AJ, et al. Journal of Foot and Ankle Surgery. 2022;61(2):369–383.
Addresses evaluation, treatment selection, pediatric considerations, and postoperative care. Identifies topics where expert consensus remains limited.
Read Consensus Statement ↗Randomized Controlled Trial | 2020
Five-Year Follow-up of Minimally Invasive Distal Metatarsal Chevron Osteotomy in Comparison with the Open Technique
Kaufmann G, Mörtlbauer L, Hofer-Picout P, et al. Journal of Bone and Joint Surgery American Volume. 2020;102(10):873–879. doi:10.2106/JBJS.19.00981.
Found comparable clinical and radiographic outcomes between minimally invasive and open chevron surgery at 5 years.
View Clinical Trial ↗Professional Patient Guidance
Minimally Invasive Bunion Surgery
American Orthopaedic Foot & Ankle Society. FootCareMD.
Explains small incision bunion correction, protected walking, recovery expectations, and possible complications.
Read MIS Surgery Guide ↗Professional Patient Guidance
Bunions: Hallux Valgus
American Orthopaedic Foot & Ankle Society. FootCareMD.
Provides an overview of bunion causes, symptoms, diagnosis, and treatment options.
Read Bunion Guide ↗Professional Recommendations
5 Things You Need to Question
American Orthopaedic Foot & Ankle Society. FootCareMD.
Explains why bunion surgery should address symptoms and activity limitations rather than appearance alone.
Read Recommendations ↗Professional Patient Guidance
Lapidus Procedure
American Orthopaedic Foot & Ankle Society. FootCareMD.
Describes fusion at the base of the first metatarsal, why it may be recommended, and recovery considerations.
Read Lapidus Guide ↗Clinical Review | 2021
Percutaneous, MIS and Open Hallux Valgus Surgery
Trnka HJ. EFORT Open Reviews. 2021;6(6):432–438. doi:10.1302/2058-5241.6.210029.
Reviews open and minimally invasive techniques, differences between generations of MIS surgery, and the importance of surgical training.
Read Open Access Review ↗Prospective Case Series | 2025
Fourth-Generation Percutaneous Transverse Osteotomies for Hallux Valgus
Lam P, Murphy EP, Chua MJ, et al. Journal of Bone and Joint Surgery American Volume. 2025;107(19):2185–2196. doi:10.2106/JBJS.24.01326.
Reports improved symptoms and alignment in a series of 729 feet. Includes recurrence and complication rates; results reflect a single surgeon’s series rather than a randomized comparison.
View Transverse Osteotomy Study ↗New 2026 Evidence | Retrospective Comparative Study
Increased Risk of Recurrence in Severe Hallux Valgus Associated With Inability to Passively Correct Deformity Prior to Surgery: A Comparative Study of Transverse vs Chevron Osteotomy Minimally Invasive Surgery Techniques
Lewis TL, Watt C, Fletcher L, et al. Foot & Ankle Orthopaedics. 2026;11(2). doi:10.1177/24730114261434234.
Examines severe bunions treated with 2 MIS techniques. Higher recurrence in the transverse group occurred alongside less preoperative flexibility, emphasizing the importance of patient selection.
View 2026 Research ↗About our sources: We prioritize peer-reviewed research and established professional guidance. Patient education pages are labeled separately from research studies. Results vary between procedures and patients, and no single study guarantees an individual outcome.
