
Updated by Dr. Dawson October 2026
TLDR
Ingrown toenails hurt, they can become infected, and they almost never “just go away.” Mild cases can sometimes be calmed at home with trimming, soaking, and better shoes, but once redness, swelling, or pus appear it’s time to call your podiatrist. In-office treatments range from a simple trim to a permanent fix.
What Is an Ingrown Toenail?
An ingrown toenail develops when the edge of the nail grows into the surrounding skin instead of straight out. This causes pain, redness, swelling, and in many cases infection. It is one of the most common nail problems we see in podiatry, accounting for up to 20% of all foot care visits¹ in primary care settings.
For many patients, an ingrown toenail is the first time they truly “notice” their toenails. One week you’re ignoring them, the next you can’t even put on socks without wincing.
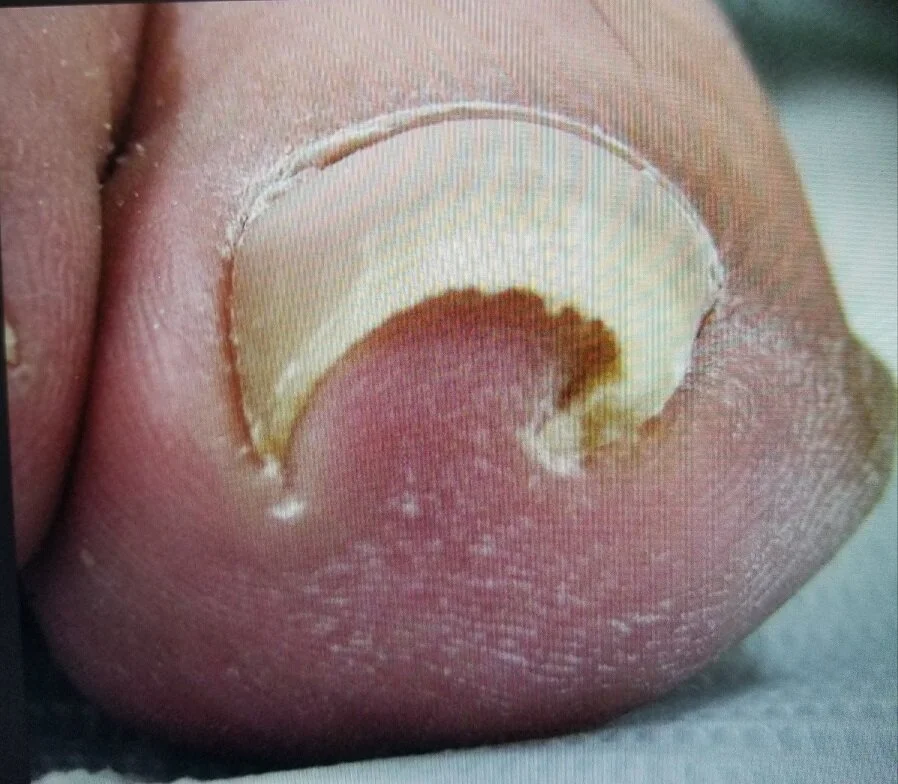
Why the corner gets angry: Thickened nails from toenail fungus and toe crowding from bunions increase pressure on the nail fold.
Why Do Toenails Become Ingrown?
There is rarely a single reason. In most cases it’s a combination of factors:
1. Trauma
Toenails are built to protect the top of the toe from direct pressure—like someone stepping on your foot. They are not built to handle sideways blows, like stubbing your toe on furniture at 3 AM. This side impact pushes the soft nail fold into the nail plate, creating a wound that the nail edge continues to aggravate.
2. Shoe Gear
Shoes that are too short, too narrow, or too pointed press the skin of the toe directly into the nail. Over time this repeated pressure leads to nail border irritation and eventual ingrowth.
3. Genetics (Born to Ingrow)
Some nails are simply too wide or too curved for the toe they sit on. Children often present during growth spurts, while older adults may develop “pincer nails” (curved like a horseshoe) with age.² Unfortunately, in these cases trimming and shoe changes can only do so much.

4 month old with an ingrown toenail. We temporarily removed the offending border in hopes that as it grows back it will get more in sync with the growing toe. This is a single case and not all infants need a procedure.
4. Nail Cutting Technique
The myth is that cutting straight across will prevent ingrowns while curving the nail invites them. In truth, both methods are fine if you’re consistent. The problem comes when corners are cut too deeply or you traumatize the nail borders while trimming. That allows the soft skin fold to collapse inward or start to swell, forcing the nail to pierce through. When in doubt, cut straight across.
5. Fungal or Thick Nails
Fungal infections often make nails thick, brittle, and distorted. This extra bulk puts pressure on the surrounding skin and raises the risk of ingrowth.³
📖 RELATED READING
Toenail Fungus: What Actually Works?
Not every thick, yellow, or damaged toenail is caused by fungus. Learn how fungal nail infections are diagnosed and which treatments are supported by medical research.
Who Gets Ingrown Toenails?
Children: Ingrown nails often appear during growth spurts (ages 9–12 and 16–20).² Babies can even present with them—sometimes the nail is simply larger than the tiny toe can accommodate.
Adults: Trauma, shoe gear, and fungal infections dominate here.
Older adults: Decades of repetitive stress can cause exaggerated nail curvature. Poor circulation also raises the stakes if infection develops.
Ingrown Nail Treatments: What Works and What Doesn’t
Ingrown Toenail Treatments Compared
From simple home care to permanent nail procedures, the best treatment depends on the severity of the ingrown nail, how often it returns, and your medical history.
| Treatment | Best For | What to Expect | Will It Return? |
|---|---|---|---|
| Conservative Home Care Nonprocedural | Mild irritation without significant swelling, pus, or severe pain. | Wider shoes, gentle hygiene, warm soaks, and avoiding deep trimming. Some patients benefit from carefully guided nail lifting. ¹ | Possible. Symptoms may resolve, but pressure or nail curvature can cause repeated episodes. |
| Professional Nail Lifting or Bracing Conservative Procedure | Selected mild to moderate ingrown nails, especially when preserving the nail is preferred. | A clinician may use taping, a gutter splint, or a nail brace to separate the nail edge from the irritated skin. ¹ | Possible. Recurrence depends on the underlying nail shape and continued pressure. |
| Slant Back Nail Trimming Office Treatment | Selected mild cases where an accessible nail corner is causing focal pressure. | A clinician trims the offending edge without intentionally destroying the nail matrix. | Yes, it can. The nail continues to grow and may irritate the same border again. |
| Temporary Partial Nail Avulsion Office Procedure | Painful or persistent cases requiring removal of an offending nail border. | The toe is numbed and the ingrown nail strip is removed. Symptoms often improve as the injured skin heals. ¹ | Higher recurrence risk. The nail matrix remains active, allowing the border to regrow. ² |
| Partial Nail Avulsion + Matrixectomy Long-Term Treatment | Recurrent, chronic, or more severe ingrown nails. | The offending nail strip is removed and the corresponding matrix is treated chemically or surgically. Healing takes weeks and drainage may occur. ⁴ | Lower recurrence risk than avulsion alone, but recurrence is not impossible. ³ |
This comparison is educational. Diabetes, neuropathy, poor circulation, spreading redness, fever, or worsening drainage warrant prompt professional evaluation. Treatment outcomes vary with nail anatomy, technique, and patient factors.
| Home Treatment | Does It Help? | Why |
|---|---|---|
| Proper trimming | ✅ | Consistent straight or curved cutting, not too short |
| Wider shoes | ✅ | Prevents pressure on the nail folds |
| Soaking in warm water/Epsom salts | ✅ | Reduces inflammation and debris |
| Cutting a V in the nail | ❌ | The nail grows from the root, not the tip |
| Bathroom surgery | ❌ | High risk of infection and incomplete removal |
Can an Ingrown Toenail Go Away on Its Own?
Yes, some mild ingrown toenails can improve without a procedure. But there's an important difference between calming an irritated nail and fixing a nail that repeatedly grows into the skin.
An early ingrown toenail usually starts with tenderness along 1 corner of the nail. You might notice mild redness or discomfort when wearing tight shoes, but there isn't significant swelling, drainage, or excessive tissue growing around the nail.
At this stage, conservative treatment may be enough to allow the nail to grow beyond the irritated skin.¹
Key takeaway: prevention beats bathroom surgery. Trim consistently, wear shoes with room in the toe box, and manage thick or curved nails early.

Is My Ingrown Toenail Infected? Do I Need Antibiotics?
A red, swollen, draining ingrown toenail looks infected. Sometimes it is.
But here's something that surprises a lot of patients: Not every angry looking ingrown toenail needs antibiotics.
An ingrown nail creates a mechanical injury. As the sharp nail edge presses into the surrounding skin, your body responds with inflammation. This can cause swelling, redness, pain, and even the development of granulation tissue, that soft, red tissue that sometimes grows over the corner of the nail.
These findings may occur with or without a bacterial infection.¹
How Can You Tell if It's Infected?
Some redness and tenderness immediately around an embedded nail can result from local inflammation. Drainage may occur with more advanced irritation, although pus can also indicate a localized infection.
Findings that raise greater concern for bacterial infection include:
Redness that is spreading beyond the immediate nail fold
Increasing warmth, swelling, or pain
Purulent drainage, especially with worsening surrounding inflammation
Red streaking extending away from the toe
Fever, chills, or feeling generally unwell
Spreading redness, fever, or rapidly worsening symptoms warrant prompt medical assessment.
Why Antibiotics Aren't Always the Answer
Here's the fundamental problem: Antibiotics don't remove the piece of nail digging into your skin.
Even if medication improves an associated bacterial infection, the mechanical irritation can continue until the offending nail border is addressed.
A randomized clinical trial published in Archives of Family Medicine evaluated 54 otherwise healthy patients with locally infected ingrown toenails. Researchers compared chemical matrixectomy alone with treatment that included oral antibiotics.
Adding oral antibiotics did not significantly improve healing time or postoperative outcomes compared with performing the procedure alone.⁶
This supports a more targeted approach to antibiotic use rather than automatically prescribing medication for every inflamed toenail.
When Are Antibiotics Appropriate?
Oral antibiotics may be necessary when an ingrown toenail is accompanied by spreading cellulitis, systemic illness, or another indication determined during examination.
Patients with diabetes, peripheral vascular disease, impaired immunity, or poor wound healing require additional consideration because the consequences of infection can be more serious.
These patients also should not assume they can safely manage a worsening ingrown toenail at home.
Should the Nail Be Removed if It's Infected?
In many otherwise healthy patients, removing the offending nail border is an important part of treating the problem, even when localized infection is present.
The choice between temporary nail removal and a permanent matrixectomy depends on the severity, history of recurrence, examination findings, and individual risks.
The bottom line: Not every red ingrown toenail requires antibiotics, and antibiotics alone often won't solve the underlying problem. Treating the nail itself may be the most important step toward getting the toe to heal.¹ ⁶
What to Expect During and After Ingrown Toenail Removal
If you've never had an ingrown toenail removed, the idea of someone cutting part of your nail out probably sounds worse than the actual procedure.
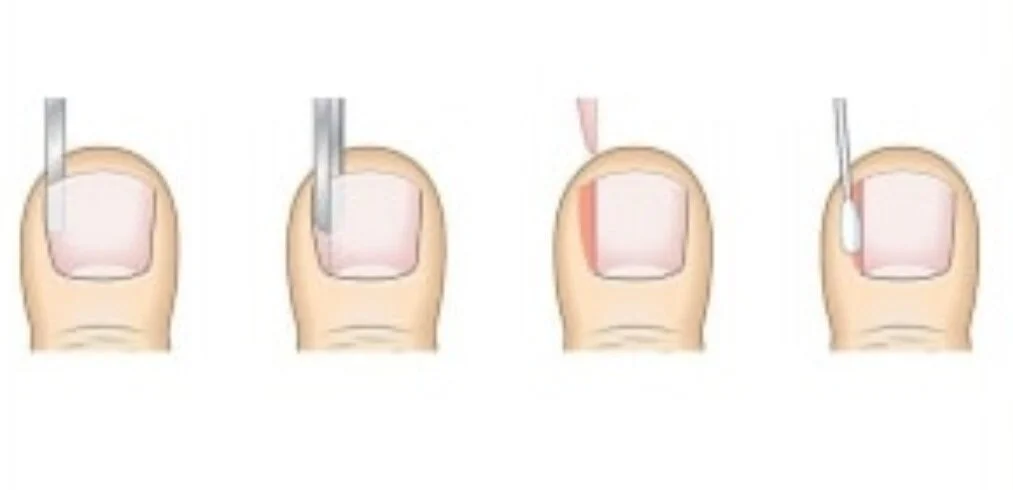
Fortunately, most ingrown toenail procedures are performed in the office using local anesthesia, and patients are typically able to walk out afterward.
Does Ingrown Toenail Removal Hurt?
For most patients, the least enjoyable part is the anesthetic injection.
A local anesthetic is injected around the base of the toe to temporarily numb the area. You can expect a brief burning or pressure sensation during the injection.
Once the anesthetic takes effect, the procedure should not cause sharp pain. You may still feel pressure or movement as the nail border is removed.
If you experience sharp pain during the procedure, tell your podiatrist so additional anesthesia can be considered.
How Long Does Recovery Take?
Recovery depends on the procedure and how quickly your body heals.
Temporary Partial Nail Removal
When the nail border is removed without treating the matrix, the irritated tissue can begin healing once the offending nail is gone.
Many patients can return to regular walking and routine daily activities relatively quickly, although tenderness may persist during the initial healing period.
Because the nail matrix remains intact, the removed border can gradually regrow. If the underlying problem persists, the nail may eventually become ingrown again.
Permanent Matrixectomy
A matrixectomy is intended to prevent the treated portion of the nail from returning.
If a chemical such as phenol is used, the treated area heals as a small wound. Mild postoperative drainage is common, and complete healing can take several weeks.
Although the procedure is designed to provide more durable relief, the wound may remain moist longer than after a simple temporary nail removal.⁴
The extent of nail tissue removed, technique used, circulation, and other medical factors can all influence recovery.
What Is Normal After the Procedure?
Some soreness, mild swelling, and a small amount of drainage are expected following many nail procedures.
After a chemical matrixectomy, clear or lightly blood tinged drainage may continue during healing. This does not automatically mean the toe is infected.
A commonly cited postoperative course includes sterile drainage for approximately 2 to 3 weeks after phenolization, although individual healing times vary.¹
Your podiatrist will provide specific wound care instructions, including when to remove the initial dressing, how to clean the area, and what type of dressing to use afterward.
Follow those instructions rather than assuming that more soaking, more antibiotic ointment, or tighter bandages will make the wound heal faster.
Can You Walk, Work, or Exercise After Nail Removal?
Most patients can walk after the procedure, although open toe or roomy footwear may be more comfortable during the first several days.
People with primarily desk based jobs may be able to return quickly. Jobs requiring prolonged standing, tight safety footwear, or extensive walking may be less comfortable initially.
Higher impact exercise, swimming, and other activities that increase pressure or expose an unhealed wound to irritation may need to be temporarily limited.
The safest timeline depends on the procedure and the condition of the toe. Follow your podiatrist's specific activity and wound care recommendations.
When Should You Call Your Podiatrist?
Contact your treating clinician if you develop:
Increasing rather than improving pain
Redness that spreads beyond the procedure site
Increasing warmth or swelling
Thick or worsening purulent drainage
Bleeding that does not stop with recommended measures
Delayed healing or a wound that appears to be getting worse
Seek urgent medical attention for rapidly spreading redness, fever, severe pain, or other systemic symptoms.
The Podiatrist's Take: The procedure itself is usually much less intimidating than patients expect. The important part is understanding that temporary nail removal and permanent matrixectomy have different goals. One removes the immediate problem. The other also attempts to prevent the offending nail border from growing back. Neither eliminates the need for appropriate wound care.
Key Takeaways
Ingrown toenails are common, painful, and often unavoidable. Sometimes you just get unlucky.
Home remedies can help in very mild cases, but infected or recurring nails need professional care.
Podiatric procedures are simple and effective, and often less painful than the ingrown itself.
Permanent removal offers lasting relief for recurrent problems.
Ingrown Toenail FAQ
Can an ingrown toenail heal without surgery?
Yes. Mild ingrown toenails may respond to wider shoes, appropriate nail care, and conservative treatments that reduce pressure on the nail fold. More advanced or recurrent cases often require professional treatment.¹
Do I need antibiotics for an infected ingrown toenail?
Not always. Localized inflammation and drainage do not automatically require oral antibiotics. Antibiotics may be appropriate when cellulitis or another clinically significant infection is present. Removing the offending nail border is often an important part of treatment.¹ ⁶
Is ingrown toenail removal painful?
The anesthetic injection may cause brief discomfort. Once the toe is numb, patients generally feel pressure rather than sharp pain during the procedure. Mild soreness afterward is expected.
How long does an ingrown toenail procedure take to heal?
Healing varies with the procedure and your medical history. Simple nail removal may heal relatively quickly, while chemical matrixectomy commonly requires several weeks. Mild drainage may persist during the healing process.¹ ⁴
Can an ingrown toenail come back after permanent removal?
Yes, although matrixectomy significantly reduces recurrence compared with simple nail avulsion. Small portions of residual nail matrix can sometimes produce recurrent nail growth.² ³
Will my toenail look normal after a permanent matrixectomy?
A partial matrixectomy intentionally prevents the treated nail border from regrowing, leaving the nail slightly narrower. Most patients retain the majority of their natural nail, but the final appearance depends on the amount of matrix treated and how the toe heals.
🦶 Recommended Products for Ingrown Toenails
These items are listed for education and reference only. They are not a substitute for medical advice. Please see your podiatrist for specific recommendations. I may receive a commission if you purchase through these links, at no additional cost to you.
🔧 Tools
- Barrel Hinged Nail Nipper – Sturdy clipper for thick or curved toenails
🧴 Skin & Nail Care
- Epsom Salts – Foot soaks to calm soreness and swelling around the nail
- Antifungal Shoe Spray – Keeps shoes clean to reduce infection risk
Research & References
Feet Made Simple is committed to evidence-based foot and ankle education. The following clinical reviews, systematic reviews, and original studies informed this article. References were reviewed in October 2026.
Ingrown Toenail Management
Mayeaux EJ Jr, Carter C, Murphy TE. American Family Physician. 2019;100(3):158-164.
Practical guidance on conservative care, nail lifting, partial avulsion, matrixectomy, and antibiotic indications.
Read Clinical Review ↗Comparative Effectiveness of Ingrown Toenail Treatments: Systematic Review and Network Meta-analysis
Morioka D, Matsuoka Y, Tamagawa K, et al. Journal of Foot and Ankle Surgery. Published online August 24, 2026. doi:10.1053/j.jfas.2026.08.021.
An analysis of 44 studies involving 5,068 patients comparing recurrence, pain, healing, and recovery across conservative and procedural treatments.
View 2026 Research ↗Surgical Treatments for Ingrown Toenails, Part I: Recurrence and Relief of Symptoms
Exley V, Jones K, O'Carroll G, Watson J, Backhouse M. Journal of Foot and Ankle Research. 2023;16:35. doi:10.1186/s13047-023-00631-1.
Evaluates recurrence following different nail procedures. Supports the role of phenol treatment in reducing recurrence compared with avulsion alone, while highlighting limitations in study quality.
Read Open Access Study ↗Surgical Treatments for Ingrown Toenails, Part II: Healing Time, Postoperative Complications, Pain, and Satisfaction
Exley V, Jones K, O'Carroll G, Watson J, Backhouse M. Journal of Foot and Ankle Research. 2023;16:55. doi:10.1186/s13047-023-00655-7.
Reviews postoperative recovery, drainage, infection, discomfort, and patient satisfaction across different surgical techniques.
Read Open Access Study ↗Interventions for Ingrowing Toenails
Eekhof JAH, Van Wijk B, Knuistingh Neven A, van der Wouden JC. Cochrane Database of Systematic Reviews. 2012;(4):CD001541. doi:10.1002/14651858.CD001541.pub3.
Found surgical approaches generally more effective than nonsurgical approaches in preventing recurrence in the trials reviewed.
View Cochrane Review ↗Are Antibiotics Necessary in the Treatment of Locally Infected Ingrown Toenails?
Reyzelman AM, Trombello KA, Vayser DJ, Armstrong DG, Harkless LB. Archives of Family Medicine. 2000;9(9):930-932. doi:10.1001/archfami.9.9.930.
In selected otherwise healthy patients, routine oral antibiotics added to a nail procedure did not improve healing time or postoperative morbidity.
Read Clinical Trial ↗Comparison of Chemical Matricectomy with Trichloroacetic Acid, Phenol, or Sodium Hydroxide
Chang HC, Lin MH. Acta Dermato-Venereologica. 2020;100(4):adv00065. doi:10.2340/00015555-3379.
Compares chemical matrixectomy agents. Suggests alternatives to phenol may be effective, although the evidence remains limited.
Read Open Access Study ↗How to Trim Your Nails
American Academy of Dermatology Association. Dermatologist-reviewed patient education resource.
Practical nail trimming advice, including cutting toenails straight across to reduce the risk of ingrown nails.
Read Nail Care Guidance ↗